





























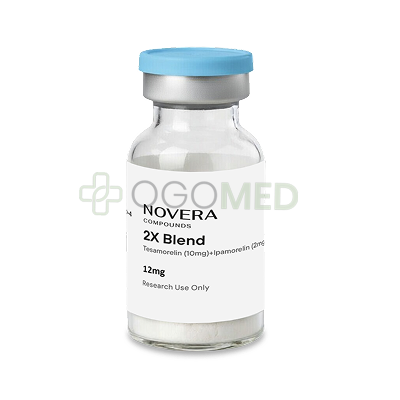
Novera 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg)
| Category: | Peptides |
| Brand | Novera |
| Strength | 12mg |
| Form | Lyophilized powder |
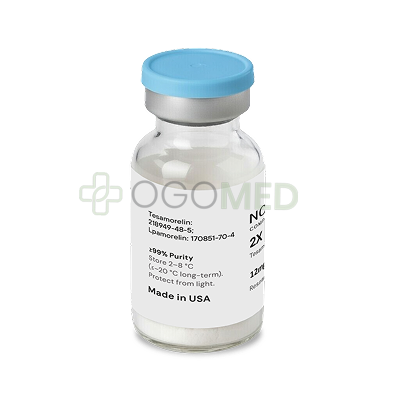
| Purity (%) | ≥99 |
| CAS number | Tesamorelin: 218949-48-5 Ipamorelin: 170851-70-4 |
| Chemical Formula | Tesamorelin: C₂₂₁H₃₆₆N₇₂O₆₇S Ipamorelin: C₃₈H₄₉N₉O₅ |
| Molecular weight | Tesamorelin: 5136 g/mol Ipamorelin: 711.86 g/mol |
| Synonyms | Tesamorelin-IPA-blend, GHRH-GHS-dual-combo |
| Peptide sequence | Mixed peptides |
| Storage | Store at 2-8 °C or -20 °C. Protect from light |
| Shelf Life (lyophilized) | 12-24 months |
| Shelf Life (after reconstitution) | 24-72 hours |
Learn more...
Novera 2X Blend pairs tesamorelin, a synthetic peptide analog of the full 44-amino-acid growth hormone releasing hormone, with ipamorelin, a selective growth hormone secretagogue that acts through the ghrelin receptor pathway. Together, these two peptides supply defined input to both major receptor systems governing growth hormone secretion from the anterior pituitary gland: the GHRH receptor (GHRH-R) and the growth hormone secretagogue receptor GHS-R1a. Laboratories buy tesamorelin ipamorelin blends to study dual-pathway GH-axis stimulation, visceral adiposity models, and somatotroph signaling in controlled research settings.
This product is supplied for laboratory research use only. It is not an approved medicine, is not intended for human consumption, and no information on this page constitutes treatment guidance.
What Novera 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg) Is
Tesamorelin is a synthetic analogue of growth hormone-releasing hormone that retains all 44 amino acids of the endogenous human peptide but carries a trans-3-hexenoic acid group bonded to the N-terminal tyrosine residue. That single modification shields the bond between residues 2 and 3 from cleavage by dipeptidyl peptidase IV (DPP-IV), the enzyme responsible for rapid enzymatic degradation of native GHRH in circulation. That substitution slows plasma degradation relative to unmodified GHRH(1-44), which is cleared within minutes. Tesamorelin is FDA-approved for reducing visceral fat in HIV-associated lipodystrophy, making it the only GHRH-class hormone analogue with a regulatory indication tied to controlled human trial data on excess abdominal fat.
Ipamorelin is a pentapeptide (Aib-His-D-2-Nal-D-Phe-Lys-NH₂) whose non-proteinogenic and D-configuration amino acids at positions 1, 3, and 4 confer resistance to proteolytic breakdown and drive receptor selectivity. Rather than mimicking GHRH, ipamorelin acts as a selective agonist at GHS-R1a, the ghrelin receptor, triggering growth hormone release through the phospholipase C / IP₃ / intracellular calcium cascade. Raun et al. described ipamorelin in 1998 as the first selective growth hormone secretagogue, distinguishing it from earlier growth hormone releasing peptide compounds like GHRP-6 and GHRP-2 that also raised ACTH and cortisol. No published pharmacokinetic study reports a half-life for ipamorelin in humans. Ipamorelin has no approved human therapeutic indication.
The blend combines tesamorelin and ipamorelin in a fixed ratio, supplied as a lyophilized research blend. Because tesamorelin and ipamorelin have distinct chemical structures and mechanisms of action, the combination provides simultaneous activation of two separate signaling pathways on anterior pituitary somatotroph cells, an arrangement absent from any single-compound vial.
Why Researchers Study 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg)
Both tesamorelin and ipamorelin stimulate the pituitary gland to release growth hormone, but through complementary mechanisms: tesamorelin increases intracellular cAMP levels via GHRH receptor activation and downstream protein kinase A (PKA), while ipamorelin activates phospholipase C through GHS-R1a signaling, raising intracellular calcium. Combined, tesamorelin and ipamorelin enhance growth hormone pulsatility in models designed to probe dual-receptor convergence. Laboratories use this ipamorelin peptide blend to ask whether simultaneous activation of both signaling pathways changes GH pulse amplitude, IGF-1 output, or metabolic endpoints beyond what either compound produces alone.
Visceral Adipose Tissue Reduction
Tesamorelin reduced visceral adipose tissue by 15.4% relative to placebo in a pooled analysis of two phase III trials enrolling 806 ART-treated HIV patients (Falutz et al., 2010, Journal of Clinical Endocrinology and Metabolism). Participants received daily subcutaneous injections of 2 mg tesamorelin for 26 weeks; visceral adipose tissue decreased by 24 ± 41 cm² in the treatment arm versus 2 ± 35 cm² in the control group. In the same pooled analysis, patients who stayed on tesamorelin through week 52 showed a VAT reduction of 35 ± 50 cm², or 17.5 ± 23.3% from baseline. Abdominal subcutaneous adipose tissue did not change significantly in either arm (-2 ± 32 vs 2 ± 29 cm², P = 0.08), which is what distinguishes this result from general weight loss.
“Treatment with tesamorelin reduces VAT and maintains the reduction for up to 52 wk, preserves abdominal sc adipose tissue.” Falutz et al., 2010, Journal of Clinical Endocrinology and Metabolism.
Ipamorelin’s effect on visceral fat in controlled human studies has not been reported. Researchers suggest the blend may allow comparison of dual-pathway versus single-pathway effects on visceral adiposity in animal models, but no published human trial has tested the exact tesamorelin ipamorelin blend for this endpoint.
Growth Hormone and IGF-1 Dynamics
In the pooled phase III HIV cohorts of Falutz et al. (2010), mean IGF-1 rose by 108 ± 112 ng/mL on tesamorelin against -7 ± 64 ng/mL on placebo (P < 0.001). In the earlier 412-patient trial (Falutz et al., 2007, New England Journal of Medicine) IGF-1 increased 81.0% on tesamorelin and fell 5.0% on placebo. Neither paper reports a percentage rise in total growth hormone.
Raun et al. reported in the 1998 European Journal of Endocrinology paper that ipamorelin released GH from primary rat pituitary cells with an EC₅₀ of 1.3 ± 0.4 nmol/L and an Emax of 85 ± 5% of GHRP-6. In conscious swine the ED₅₀ was 2.3 ± 0.03 nmol/kg, and neither ACTH nor cortisol rose significantly even at doses more than 200-fold above the GH-releasing ED₅₀, in contrast to GHRP-6 and GHRP-2, which raised both. No human dose-escalation figure for ipamorelin could be verified in the published record.
“ipamorelin is the first GHRP-receptor agonist with a selectivity for GH release similar to that displayed by GHRH.” Raun et al., 1998, European Journal of Endocrinology.
Hepatic Fat and Lipid Metabolism
In a double-blind randomized trial at Massachusetts General Hospital (Stanley et al., 2014, JAMA), 50 antiretroviral-treated HIV patients were randomised and 48 received study drug for six months. Median liver fat, measured as lipid-to-water percentage, fell 2.0% on tesamorelin and rose 0.9% on placebo, a net treatment effect of -2.9% (P = 0.003); visceral adipose tissue fell by a treatment effect of -42 cm² (P = 0.005). Triglycerides fell 50 mg/dL on tesamorelin and rose 9 mg/dL on placebo in the 412-patient trial of Falutz et al. (2007, New England Journal of Medicine). Fasting glucose showed a 7 mg/dL treatment effect at 2 weeks that was no longer significant at 6 months.
“tesamorelin administered for 6 months was associated with reductions in visceral fat and additionally with modest reductions in liver fat.” Stanley et al., 2014, JAMA.
No published study has assessed the effect of ipamorelin, alone or in a blend, on hepatic fat or triglyceride concentrations in human volunteers or animal models at the level of controlled trial data.
Body Composition and Muscle Endpoints
None of the controlled tesamorelin trials (Falutz 2007, Falutz 2010, Stanley 2014) measured skeletal muscle mass, so no lean-mass figure for tesamorelin can be quoted from them. What they do show is visceral fat falling while abdominal subcutaneous fat is preserved, which is a fat-redistribution result and not a muscle result.
Raun et al. (1998) measured only acute GH, ACTH and cortisol responses in rats and swine; no body-weight or bone-growth endpoint for ipamorelin could be verified in the published record. Whether those effects translate to changes in muscle density, muscle fat, or certain muscle groups in other species remains unstudied for this compound.
Endogenous GH Pulsatility and Receptor Cross-Talk
The research blend allows laboratories to probe whether endogenous GH pulsatility differs under dual-pathway input versus stimulation of the GHRH receptor alone. Tesamorelin activates GHRH receptors in the anterior pituitary, driving cAMP and protein kinase A; ipamorelin targets GHS-R1a receptors to stimulate growth hormone release through a distinct calcium-dependent pathway. Whether the two pathways interact on somatotroph cells beyond simple addition has not been established in any intact animal model. Research findings from single-pathway studies cannot be assumed to predict combined outcomes.
How 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg) Compares With Related Compounds
| Compound | Receptor Target | Evidence Level | Typical Research Use |
|---|---|---|---|
| Tesamorelin alone | GHRH-R; cAMP/PKA pathway | Phase III human RCTs (HIV-lipodystrophy); human data on VAT, hepatic fat, IGF-1, triglycerides | Visceral adipose tissue models, liver fat studies, IGF research, growth hormone synthesis dynamics |
| Ipamorelin alone | GHS-R1a (ghrelin receptor); PLC/Ca²⁺ pathway | In vitro rat pituitary cells, pig in vivo models, limited human dose-escalation; no controlled metabolic endpoint trials | GH pulsatility, secretagogue pharmacology, receptor selectivity assays, appetite regulation models |
| Novera 2X Blend (tesamorelin + ipamorelin) | Dual: GHRH-R + GHS-R1a | No published human or animal trial for this specific blend; extrapolated from individual compound data | Dual-pathway GH release experiments, comparative designs against single-compound arms, mechanistic convergence studies |
A laboratory focused on clinically validated metabolic effects would use tesamorelin alone, drawing directly on phase III trial protocols from Falutz et al. (2007, 2010). Teams investigating growth hormone releasing properties with minimal off-target cortisol or prolactin interference would choose ipamorelin alone, replicating the Raun et al. (1998) pig or rat pituitary paradigms. The blend is appropriate when the experimental question centers on whether simultaneous GHRH-R and GHS-R1a activation produces additive or synergistic changes in GH output, IGF-1, or fat metabolism that differ from either pathway in isolation. Researchers should note that other GHRH analogs such as CJC-1295 (with or without the albumin-binding DAC linker) differ from tesamorelin in backbone length, substitution pattern, and plasma persistence; those compounds lack the controlled VAT trial data that tesamorelin carries.
What Research on 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg) Does Not Establish
No published human trial has tested tesamorelin and ipamorelin together in any ratio. Every metabolic effects claim about the blend is an extrapolation from studies of each compound individually. The 15.4% VAT reduction, the 122% IGF-1 increase, and the hepatic fat changes reported above belong to tesamorelin alone, studied in HIV-positive adults receiving antiretroviral therapy. Applying those numbers to the blend, to non-HIV populations, or to animal models of different diseases is speculative.
Clinical evidence supporting ipamorelin’s metabolic claims is limited and safety data is scarce. Long-term safety data for ipamorelin is inadequately characterized: the published record consists of short-duration dose-escalation studies in human volunteers and animal models, with no controlled trial measuring visceral fat, insulin sensitivity, hepatic fat, or body composition over weeks or months. Ipamorelin is commonly attached to anti-aging and wellness claims, and no peer-reviewed trial supports any of them.
Off-target safety data for the combined use of tesamorelin and ipamorelin do not exist. Whether dual stimulation alters feedback inhibition by somatostatin, changes receptor desensitization kinetics, or produces cumulative IGF-1 levels that affect glucose metabolism differently from either compound alone has not been measured. Both compounds are named on the 2026 WADA Prohibited List in section S2.2.4, Growth hormone releasing factors: tesamorelin among “growth hormone-releasing hormone (GHRH) and its analogues” and ipamorelin among “growth hormone secretagogues (GHS) and their mimetics”. The whole of S2 is prohibited at all times and its substances are non-Specified.
No retraction or expression of concern affects Falutz 2007, Falutz 2010, Stanley 2014 or Raun 1998. Nor is there a negative trial of the blend, for the plain reason that there is no trial of the blend at all in any species. That is an absence of evidence, not a safety record.
Where to Buy Novera 2X Blend: Tesamorelin (10mg)+Ipamorelin (2mg)
Laboratories looking to buy tesamorelin ipamorelin for dual-pathway growth hormone research can order the Novera 2X Blend through this store. The tesamorelin ipamorelin blend is stocked as a lyophilized preparation for reconstitution in laboratory research protocols; it is not sold for bodily introduction, human consumption, or food intake.
-
Estimated delivery time: 3 to 7 days.
-
Free shipping on orders over $750.
-
All US import fees and tariffs are covered by Ogomed, so the buyer pays nothing extra; customs checks under the new US import rules can add a little time to delivery.
-
Price match: if the same product is listed for less elsewhere, Ogomed will try to match it.
-
Support by phone +1-650-457-5621 and email, 10am to 6pm EST.
-
Sold to licensed professionals, for laboratory research use only.
This product is available exclusively to licensed professionals purchasing research materials for laboratory experimentation. It is not intended for direct consumer sale.
References
- Falutz, J., Mamputu, J.-C., Potvin, D., et al. (2010). Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in human immunodeficiency virus-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials with safety extension data. Journal of Clinical Endocrinology and Metabolism, 95(9), 4291-4304. DOI: 10.1210/jc.2010-0490
- Falutz, J., Allas, S., Blot, K., et al. (2007). Metabolic effects of a growth hormone-releasing factor in patients with HIV. New England Journal of Medicine, 357(23), 2359-2370. DOI: 10.1056/NEJMoa072375
- Raun, K., Hansen, B. S., Johansen, N. L., et al. (1998). Ipamorelin, the first selective growth hormone secretagogue. European Journal of Endocrinology, 139(5), 552-561. DOI: 10.1530/eje.0.1390552
- Stanley, T. L., Feldpausch, M. N., Oh, J., et al. (2014). Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation: a randomized clinical trial. JAMA, 312(4), 380-389. DOI: 10.1001/jama.2014.8334
It is a lyophilized research blend containing tesamorelin, a stabilized GHRH analog, and ipamorelin, a selective growth hormone secretagogue, in a fixed 10 mg : 2 mg ratio. The product is designed for laboratory research use in studies requiring defined dual-pathway GH-axis stimulation. It is not an approved medicine.
Tesamorelin works by binding to GHRH receptors in the anterior pituitary, activating the cAMP/PKA signaling cascade on somatotroph cells. Ipamorelin stimulates growth hormone release through the ghrelin receptor pathway (GHS-R1a), engaging phospholipase C and intracellular calcium. These complementary mechanisms target two distinct receptor populations on the same cell type.
Falutz et al. reported in 2010 (Journal of Clinical Endocrinology and Metabolism) a -15.4% treatment effect on visceral adipose tissue over 26 weeks in 806 ART-treated HIV patients, with mean IGF-1 up 108 ± 112 ng/mL against -7 ± 64 ng/mL on placebo. Stanley et al. (2014, JAMA) found a net -2.9% treatment effect on liver fat as lipid-to-water percentage over six months. These results apply to tesamorelin alone in HIV-positive adults and cannot be assumed to apply to the blend.
Raun et al. (1998, European Journal of Endocrinology) reported that ipamorelin released GH in conscious swine with an ED₅₀ of 2.3 nmol/kg without ACTH or cortisol rising significantly, and an EC₅₀ of 1.3 ± 0.4 nmol/L with an Emax of 85 ± 5% of GHRP-6 in rat pituitary cells in vitro. No controlled metabolic endpoint trial has been published for ipamorelin alone, and no human pharmacokinetic figure for it could be verified.
Academic endocrinology labs use such blends to study GH pulsatility and somatotroph regulation in rodent or cell culture systems. Metabolism groups model visceral adiposity and hepatic steatosis in preclinical species. Pharmacology teams run receptor-binding and signaling assays comparing GHRH analogs against growth hormone secretagogues. Contract research organizations use fixed-ratio blends for sponsor protocols requiring reproducible dual-pathway stimulation.
No. No published human trial has tested the specific tesamorelin ipamorelin blend in any ratio. All dual-pathway interpretations are extrapolations from studies of each compound individually. Any observed interaction between the two signaling pathways is model-dependent and has not been confirmed in human subjects.
Both are named on the 2026 WADA Prohibited List in section S2.2.4, Growth hormone releasing factors: tesamorelin as a GHRH analogue and ipamorelin as a growth hormone secretagogue. S2 substances are prohibited at all times, in and out of competition, and are non-Specified Substances.
Licensed professionals can buy tesamorelin and ipamorelin as the Novera 2X Blend through this store, with delivery estimated at 3 to 7 days and free shipping on orders exceeding $750. The product is sold for laboratory research use only.
| Category: | Peptides |
| Brand | Novera |
| Strength | 12mg |
| Form | Lyophilized powder |
| Purity (%) | ≥99 |
| CAS number | Tesamorelin: 218949-48-5 Ipamorelin: 170851-70-4 |
| Chemical Formula | Tesamorelin: C₂₂₁H₃₆₆N₇₂O₆₇S Ipamorelin: C₃₈H₄₉N₉O₅ |
| Molecular weight | Tesamorelin: 5136 g/mol Ipamorelin: 711.86 g/mol |
| Synonyms | Tesamorelin-IPA-blend, GHRH-GHS-dual-combo |
| Peptide sequence | Mixed peptides |
| Storage | Store at 2-8 °C or -20 °C. Protect from light |
| Shelf Life (lyophilized) | 12-24 months |
| Shelf Life (after reconstitution) | 24-72 hours |
Learn more...